
Deep Vein Thrombosis
Deep Vein Thrombosis (DVT) refers to the development of a thrombus within a deep vein, most commonly in the leg. It can cause leg pain, swelling, warmth or skin colour changes, although some people have no symptoms. A DVT can become dangerous if part of the clot travels to the lungs and causes a pulmonary embolism (PE). Accurate diagnosis therefore matters. This article explains the symptoms, causes and risk factors for DVT, including prolonged sitting and long-distance travel. It also covers the tests used to diagnose DVT, the role of duplex ultrasound and The Whiteley Protocol®, and current approaches to treatment and follow-up.
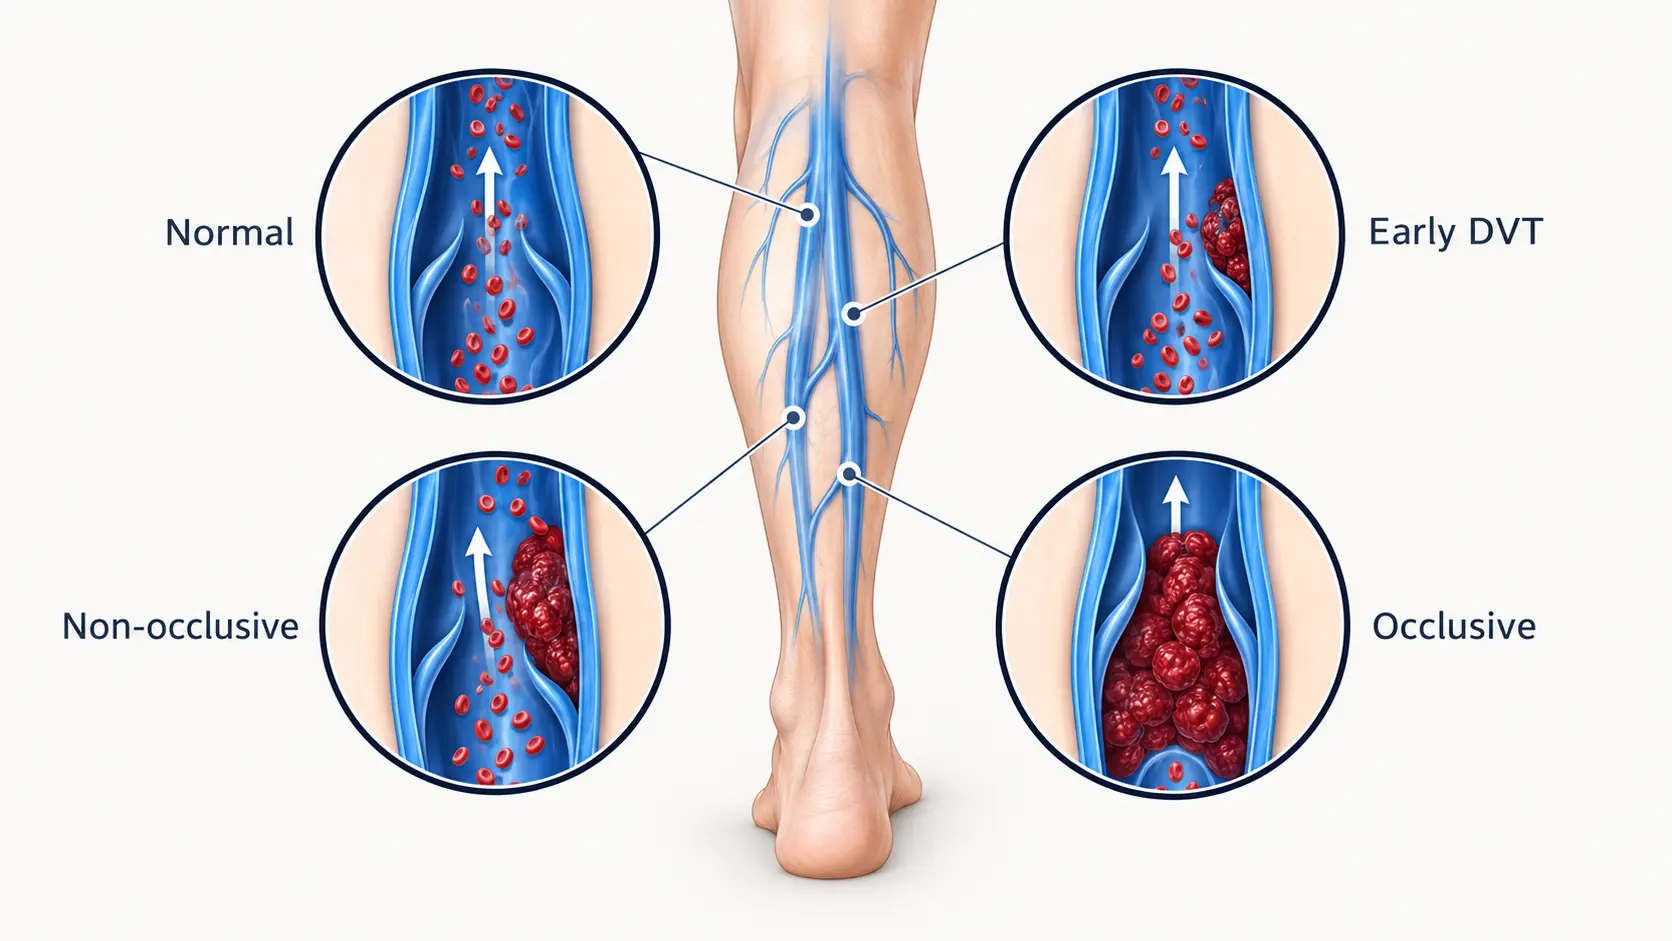
What Happens During Deep Vein Thrombosis?
Deep veins carry blood from the legs back towards the heart. Blood normally flows through these veins without clotting. However, several factors can disturb this balance and allow a thrombus to form.
A clot may remain in the leg and gradually break down. In some cases, however, part of the clot can detach and travel through the bloodstream to the lungs. This causes a pulmonary embolism, which can be life-threatening.
DVT can also cause longer-term damage. The clot may injure the deep veins and their valves, leading to persistent swelling, discomfort and skin changes. This can contribute to post-thrombotic syndrome (PTS) and, in severe cases, venous ulceration.
What Are the Symptoms of Deep Vein Thrombosis?
DVT does not always cause obvious symptoms. Around half of people with DVT may have no symptoms, according to the CDC.
When symptoms occur, they can include:
- Swelling in one leg, particularly around the calf or ankle
- Unexplained pain or tenderness in the leg
- A heavy or aching sensation, especially when standing or walking
- Warmth over the affected area
- Redness or darker skin discolouration
- Swelling that extends from the calf into the thigh
DVT usually affects one leg, although both legs can occasionally become involved.
A DVT can also occur without typical leg symptoms. Therefore, symptoms alone cannot confirm or exclude the diagnosis.
What Causes Deep Vein Thrombosis?
Deep Vein Thrombosis develops when several changes within the venous system allow a blood clot to form and grow. These changes are commonly described through Virchow’s triad, which includes reduced blood flow, changes to the vein wall and increased blood clotting tendency.
The process is more complex than simply having “thick blood”. Local changes in blood flow and the behaviour of the vein wall can create an environment in which clotting becomes more likely.
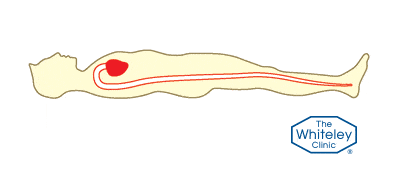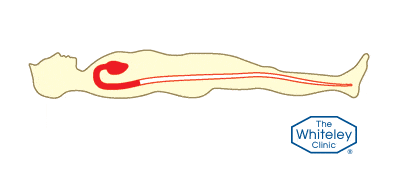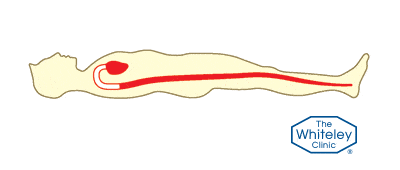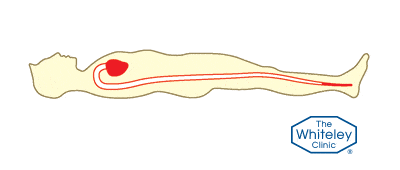
- Blood Flow in Arteries
- Blood Flow in Veins
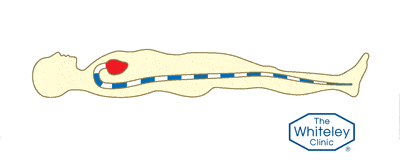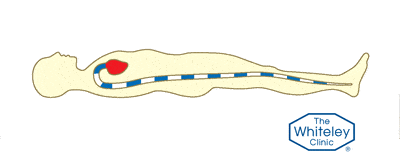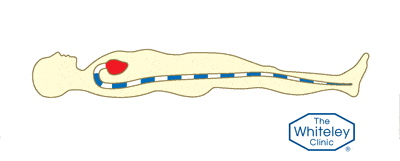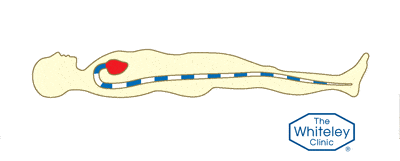
- Blood Flow in Leg Veins when sitting & standing
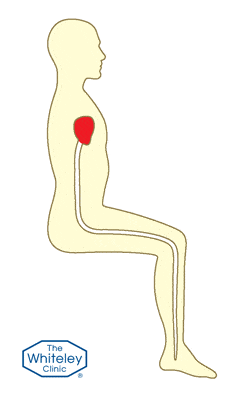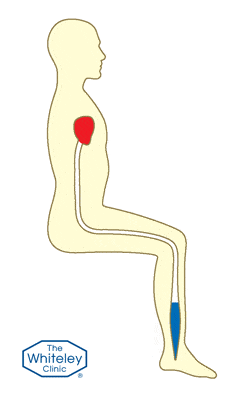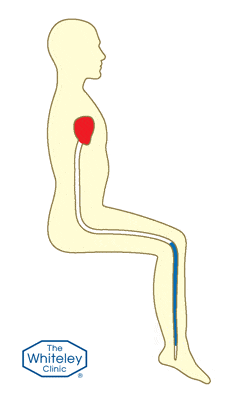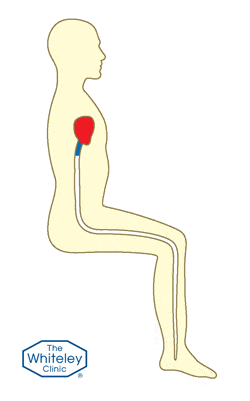
Where Does a DVT Begin?
Many lower-limb DVTs begin around the pockets of the venous valves, particularly in the calf veins. These areas naturally have slower and more complex blood flow. When venous flow becomes very slow, oxygen levels around the valve pocket can fall. This can alter the behaviour of the endothelium, the specialised cell layer lining the inside of the vein.
A healthy endothelium normally helps prevent unnecessary clotting. When it becomes activated by factors such as stasis, inflammation or local hypoxia, it can become more pro-thrombotic. This can help initiate the chain of reactions that produces a thrombus.
What Role Does Venous Reflux Play?
Venous reflux occurs when a vein valve does not close effectively, allowing blood to flow backwards. This can increase venous pressure and alter the normal pattern of blood flow.
Chronic venous reflux can affect the vein wall and surrounding tissues. Changes in shear stress and venous pressure can also influence endothelial function and inflammatory pathways.
Reflux does not mean that a DVT will develop. However, abnormalities in venous flow may contribute to venous stasis in some patients, particularly when other risk factors are present.
This is one reason why a patient may have underlying venous disease without obvious varicose veins on the skin. Abnormal reflux can involve deeper veins, perforator veins or other parts of the venous system that cannot be assessed reliably by looking at the leg alone.
How Does a Blood Clot Actually Form?
When blood flow becomes markedly reduced, the local environment within the vein can change. Stasis and reduced oxygen levels can activate the endothelium and alter the balance between natural anti-clotting and pro-clotting mechanisms.
This can promote the interaction of blood cells, coagulation proteins and the vein wall. The coagulation cascade then generates thrombin, which converts fibrinogen into fibrin. The fibrin forms a mesh that traps blood cells and helps create the developing thrombus.
The clot can remain localised or extend along the vein. If part of it breaks away, it can travel through the venous circulation to the lungs and cause a pulmonary embolism.
Can Hidden Venous Disease Increase DVT Risk?
Visible varicose veins are only one possible sign of venous disease. Some patients can have abnormal venous flow or reflux without prominent surface veins.
Venous obstruction can also affect blood flow. For example, compression of a deep vein in the pelvis can restrict venous outflow and contribute to stasis. In selected patients, structural abnormalities such as iliac vein compression may therefore be relevant when investigating venous problems.
However, hidden venous disease should not be considered a single or direct cause of DVT. Deep Vein Thrombosis usually results from an interaction between venous flow, the vein wall and the blood’s tendency to clot.
What Lifestyle Factors Can Promote Venous Stasis?
Long periods of inactivity can significantly reduce the calf muscle pump. Sitting for hours at a computer or television, remaining in bed during illness or having limited mobility after surgery or injury can therefore slow venous blood flow.
Smoking can affect vascular function and is associated with an increased risk of venous thromboembolism.
Excessive alcohol intake may contribute to fluid loss and prolonged inactivity. High caffeine intake can increase urine production in some circumstances, although caffeine itself is not an established major cause of DVT.
Inadequate fluid intake can cause dehydration, which may theoretically increase blood viscosity. However, current evidence does not establish dehydration as a direct cause of travel-associated VTE.
The effect of lifestyle factors can become more relevant when they occur alongside other recognised risk factors.
Other Important Risk Factors
Several medical and physiological factors can increase the risk of Deep Vein Thrombosis. These include:
- Recent major surgery or trauma, particularly when recovery involves reduced mobility
- Previous DVT or pulmonary embolism, which increases the risk of another clot
- Active cancer, because some cancers and cancer treatments can increase blood clotting
- Pregnancy and the post-partum period, when natural changes in blood clotting and venous flow occur
- Oestrogen-containing contraception or hormone replacement therapy, which can increase the tendency for blood to clot
- Obesity, which is associated with a higher risk of VTE
- Inherited or acquired clotting disorders, including some forms of thrombophilia
- Increasing age, as the risk of VTE generally rises with age
No single factor determines the risk of developing DVT. Several factors can occur together and increase the overall likelihood of developing a DVT.
What Is Economy Class Syndrome or Traveller's Thrombosis?
Long-distance travel can increase the risk of DVT because passengers may remain seated for several hours with limited leg movement. This is sometimes called Economy Class Syndrome or Traveller's Thrombosis.
The risk does not apply only to air travel. Long journeys by car, coach and train can also involve prolonged sitting. The CDC identifies journeys lasting more than four hours as a relevant period of prolonged travel.
Regular movement is therefore important. Walking periodically, moving the ankles and exercising the calf muscles can help maintain venous blood flow. People with additional risk factors should discuss individual preventive measures with a healthcare professional.
How Is Deep Vein Thrombosis Diagnosed?
DVT diagnosis starts with the clinical assessment. Current NICE guidance recommends the two-level DVT Wells score to estimate the clinical probability of DVT.
A D-dimer blood test may then help exclude DVT in appropriate patients. A positive result does not confirm DVT because D-dimer can rise for many other reasons.
When imaging is required, duplex ultrasound is the main diagnostic test. It can assess the deep veins and detect abnormalities in venous blood flow and the presence of thrombus.
The quality of the examination matters, particularly when a small calf DVT is suspected. An appropriately trained vascular specialist should therefore perform a detailed venous examination using suitable high-resolution equipment.
Why Is Duplex Ultrasound Important After DVT Treatment?
Duplex ultrasound is not only useful at the point of diagnosis. Follow-up imaging can also provide important information about the condition of the veins after treatment.
A follow-up scan may assess whether thrombus remains, whether the vein has reopened and whether residual venous obstruction or other abnormalities are present. These findings can contribute to decisions about ongoing management.
However, a normal follow-up scan alone should not prompt clinicians to stop anticoagulation. Current treatment decisions depend on factors such as whether the DVT (Deep Vein Thrombosis) was provoked or unprovoked, the risk of recurrence and the risk of bleeding. NICE recommends considering continued anticoagulation beyond three months after an unprovoked DVT or PE when appropriate.
How Does The Whiteley Protocol® Approach DVT?
The Whiteley Protocol® uses detailed venous duplex ultrasound as part of the assessment of venous disease.
Within this approach, the venous system is mapped in detail before treatment decisions are made. For suspected DVT, the assessment can examine the veins along the leg and, where clinically appropriate, extend the examination towards the pelvis.
The purpose is to identify venous abnormalities accurately and provide information that can support an individualised treatment plan. Duplex ultrasound can also help assess the veins after treatment and identify persistent thrombus or venous damage.
How Do Doctors Treat Deep Vein Thrombosis?
The main treatment for confirmed DVT is anticoagulation. Anticoagulants reduce the ability of the blood to form new clots and prevent an existing clot from growing while the body gradually breaks it down.
Current NICE guidance recommends direct oral anticoagulants such as apixaban or rivaroxaban for many adults with proximal DVT or PE. Other anticoagulants may be appropriate when these medicines are unsuitable.
Treatment duration depends on the individual clinical situation. A temporary provoking factor, such as surgery, may support a different treatment duration from an unprovoked DVT. Active cancer, recurrence risk and bleeding risk also influence management.
More specialised treatment may occasionally be considered for extensive or severe DVT. Options can include catheter-based procedures in carefully selected patients. Inferior vena cava filters have a limited role and are not routinely used when effective anticoagulation is possible.
What Is an Unprovoked Deep Vein Thrombosis?
An unprovoked DVT occurs when there is no recent major temporary risk factor, such as major surgery, significant immobility, trauma, pregnancy or relevant hormonal treatment.
An unprovoked DVT can sometimes be associated with an underlying condition, including cancer. However, current NICE guidance does not recommend extensive cancer screening for every person with an unprovoked DVT.
Instead, clinicians should review the medical history, perform an appropriate physical examination and review baseline blood tests. Further cancer investigations should depend on relevant symptoms or clinical signs.
When Should DVT Be Assessed Urgently?
A painful or swollen leg with unexplained warmth or skin colour change requires prompt medical assessment, particularly when several symptoms occur together.
Emergency assessment is required if symptoms suggest a pulmonary embolism. These can include sudden breathlessness, chest pain, coughing up blood, a rapid or irregular heartbeat, dizziness or fainting.
Early assessment helps clinicians select the appropriate clinical pathway, blood tests and imaging. Most importantly, clinicians should not diagnose or exclude a suspected DVT (Deep Vein Thrombosis) based on symptoms alone.