
How Can You Effectively Treat Calluses and Corns on Feet?
August 15, 2026
Varicose Veins in Pregnancy are common and often become more visible as pregnancy progresses. Hormonal changes, increased blood volume and changes in venous function can all contribute. Pregnancy can also make pre-existing venous reflux more noticeable. Although most pregnancy-related varicose veins are not dangerous, painful or inflamed veins require medical assessment. Understanding why veins change during pregnancy can help guide appropriate treatment during and after pregnancy.

Pregnancy can trigger new varicose veins, but it can also make veins that were already affected by venous insufficiency much more noticeable. A woman may have underlying venous reflux before becoming pregnant without having obvious surface veins or significant symptoms.
Venous reflux occurs when valves inside a vein do not close effectively. Blood can then flow backwards and collect in the vein. Over time, this increases venous pressure and can contribute to vein enlargement.
Pregnancy can amplify these changes. Hormonal fluctuations can affect the vein wall and surrounding connective tissue. At the same time, circulating blood volume rises substantially. The growing uterus and reduced venous efficiency can further increase the workload on the venous system. These changes may expose venous reflux that was previously difficult to see.
Pregnancy itself can also increase the likelihood of developing varicose veins. A systematic review found that women with a history of pregnancy had higher odds of developing varicose veins than women without a history of pregnancy.
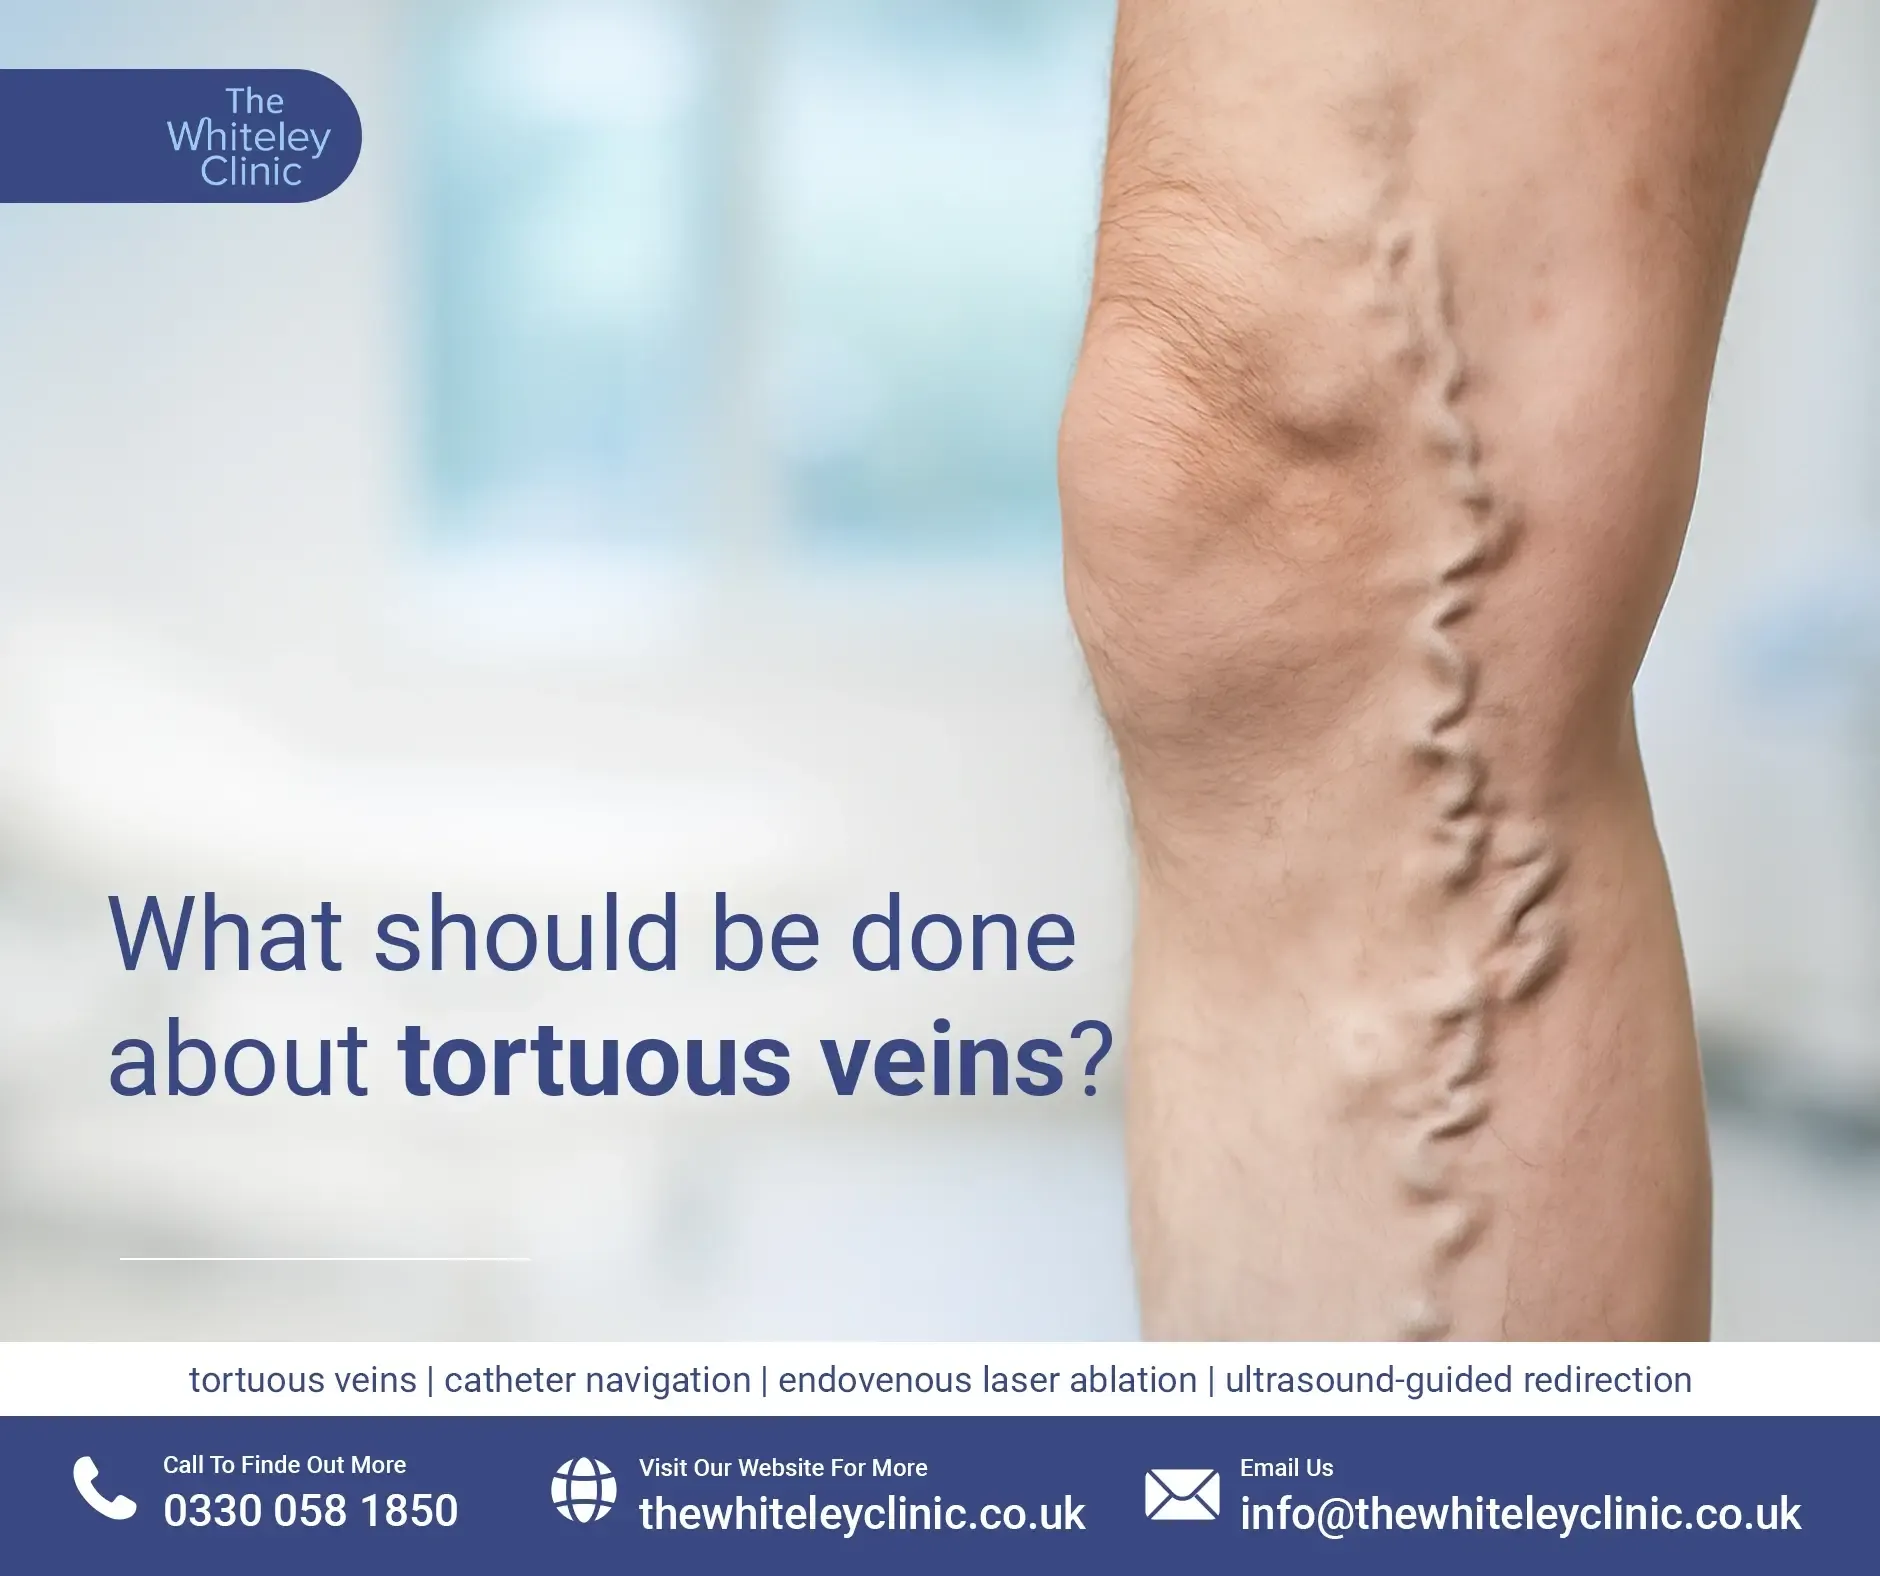
Varicose veins may appear as twisted blue or purple veins on the calves, thighs or behind the knees. Spider veins can also develop. Some women develop vulval varicosities, which may cause pressure, heaviness or discomfort around the vulva.
Varicose veins and DVT are not the same condition and should not be confused with each other.
DVT occurs when a blood clot forms in a deep vein, usually in the leg or pelvis. Part of the clot can break away and travel to the lungs, causing a pulmonary embolism. Pregnancy and the postpartum period increase the risk of venous thromboembolism because pregnancy produces physiological changes that favour blood clotting.
However, uncomplicated varicose veins do not mean that a DVT is present. Risk assessment considers the woman's complete clinical picture rather than pregnancy varicose veins alone.
Superficial thrombophlebitis involves inflammation and thrombosis within a superficial vein. It can cause a vein to feel hard, tender and cord-like. The surrounding skin may become red, warm and painful.
DVT is different because the clot forms in a deep vein. It can therefore have more serious consequences, particularly if the clot embolises to the lungs.
The two conditions can also present differently. Superficial thrombophlebitis usually produces localised redness and tenderness along a visible or palpable superficial vein. DVT may cause swelling, pain or tenderness in the affected limb, although symptoms can vary and some cases have few obvious signs.
Importantly, clinicians should not simply dismiss superficial thrombophlebitis as harmless. NICE recommends referral to a vascular service for people with superficial vein thrombosis and suspected venous incompetence.
Any pregnant woman with symptoms suggestive of DVT, such as new unilateral leg swelling or significant unexplained leg pain, requires prompt medical assessment.
Dr Karen Morton, consultant obstetrician and gynaecologist and founder of Dr Morton's – the medical helpline, how distressing pregnancy varicose veins can be. Her original guest article for The Whiteley Clinic also discussed why pregnancy does not necessarily create venous problems from scratch.
Her explanation focused on hormonal changes, increased circulating blood volume and genetic susceptibility. She also noted that vulval varicosities can look alarming but often become much less prominent after delivery.
This distinction remains important. A visible vein during pregnancy does not always represent a new disease. Pregnancy may simply make an underlying venous problem much easier to see.
Treatment options for varicose veins during pregnancy are limited. NICE CG168 recommends explaining how pregnancy can affect varicose veins and advises against interventional treatment during pregnancy, except in exceptional circumstances. Compression hosiery may help relieve symptoms such as swelling and discomfort.
Simple measures can also make symptoms more manageable. Regular movement, avoiding prolonged standing and elevating the legs when resting may help reduce discomfort and leg swelling.
Vulval varicosities can be particularly uncomfortable. However, they often become less prominent after delivery as pregnancy-related changes in the venous system gradually resolve.
In the past, doctors often advised women to delay treatment until they had completed their families. The limitations of traditional vein stripping partly influenced this approach, as the procedure involved surgically removing the affected vein.
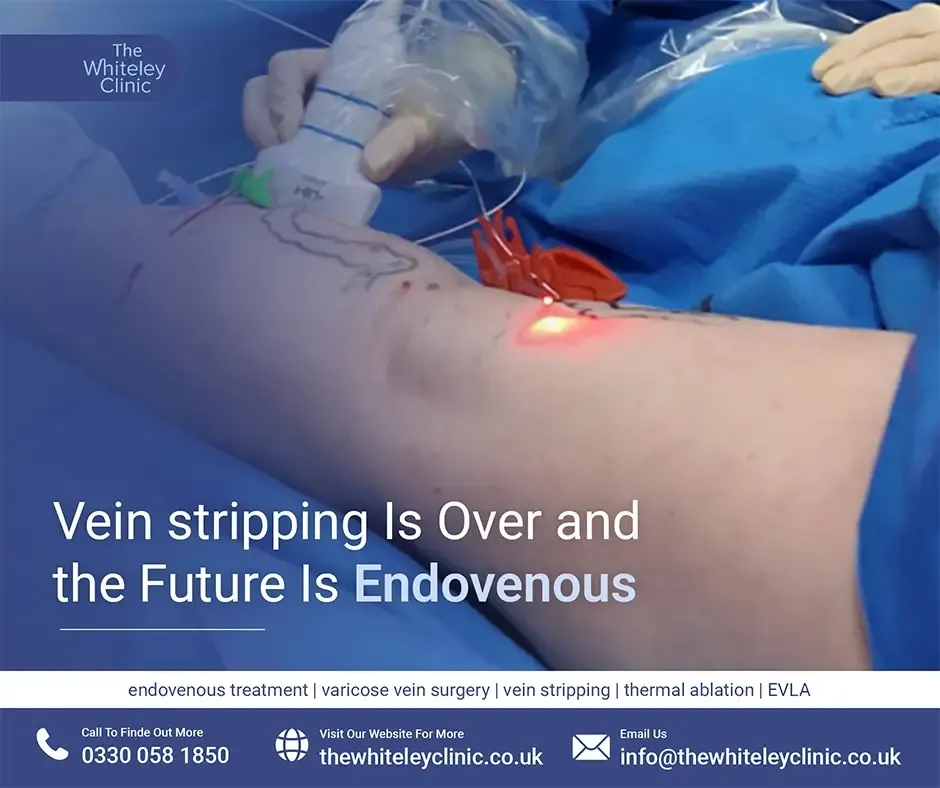
Treatment has since evolved considerably. Modern endovenous techniques can close refluxing veins without surgically removing them. These procedures include endothermal ablation and ultrasound-guided foam sclerotherapy, depending on the underlying venous anatomy and clinical findings.
For women who develop Varicose Veins in Pregnancy, treatment is generally considered after delivery rather than during pregnancy. If significant varicose veins were present before pregnancy, assessment and treatment before a planned pregnancy may also be appropriate, particularly when symptoms are troublesome or venous reflux has been confirmed.
A duplex ultrasound can identify the veins responsible for reflux and help determine whether treatment is appropriate. This is particularly important because pregnancy may make previously mild or less visible venous disease much more noticeable.
Some veins that become prominent during pregnancy may become less visible after delivery. However, this does not necessarily mean that the underlying venous reflux has resolved. Pregnancy can make previously mild or less visible venous disease much more noticeable, so persistent veins or symptoms may indicate an underlying problem that remains after delivery.
If pregnancy varicose veins, swelling, pain or vulval varicosities persist after pregnancy, a specialist venous assessment may be appropriate. A duplex ultrasound can assess venous reflux and help determine whether further treatment is needed.
For women with persistent symptomatic varicose veins, treatment options after pregnancy may include endothermal ablation, ultrasound-guided foam sclerotherapy or, when appropriate, surgery. The most suitable approach depends on the underlying venous anatomy and the findings of the duplex ultrasound.
Women with persistent symptomatic varicose veins may consider assessment and treatment before a subsequent pregnancy. This can identify underlying venous reflux and establish whether intervention is appropriate.
Previous vein stripping does not necessarily prevent successful treatment. Recurrent varicose veins can be more complex, but duplex ultrasound can help identify the underlying venous anatomy and guide management.
For detailed recommendations, see the NICE guideline CG168 on Varicose Veins: Diagnosis and Management. NICE recommends specialist assessment and duplex ultrasound for people with symptomatic varicose veins and suspected venous incompetence.
Varicose Veins in Pregnancy are often influenced by changes that affect the venous system during pregnancy. Some veins develop during pregnancy, while others become visible because pregnancy increases the pressure and physiological demands on an already vulnerable venous system. Most cases do not cause serious complications. However, persistent symptoms, inflammation or signs suggestive of DVT should never be ignored. Proper assessment can identify venous reflux and help determine whether treatment is appropriate during pregnancy or after delivery.