
How Can You Effectively Treat Calluses and Corns on Feet?
August 15, 2026
Why do varicose veins come back? the answer is more complex than simply saying that treatment has failed. Varicose veins can recur when the original source of venous reflux was not fully identified, when another refluxing vein remains untreated, or when venous disease progresses over time. Recanalisation, neovascularisation, incompetent perforator veins and pelvic venous reflux can also contribute. A detailed duplex ultrasound assessment is therefore essential when investigating recurrent varicose veins.
The subject was explored by Professor Mark Whiteley during a lecture at the Royal Society of Medicine on 19 January 2016, presented to the Independent Doctors Federation alongside Professor Deen Jameel. The lecture examined why varicose veins may return after treatment and highlighted several factors that can increase the risk of recurrence.

Current European guidelines identify several possible causes of recurrent varicose veins, including:
A thorough duplex ultrasound scan plays a central role in diagnosing venous reflux and planning treatment. NICE recommends duplex ultrasound to confirm varicose veins, assess truncal reflux and plan treatment in people with suspected primary or recurrent disease.
A comprehensive examination should do more than locate the visible veins. It should trace reflux to its source and assess the relevant superficial, deep and perforating veins. The 2023 SVS/AVF/AVLS guidelines specifically recommend tracing superficial reflux to its source, including the saphenous junctions, truncal veins, perforators and, where relevant, pelvic-origin varicose veins.
This is particularly important after previous treatment. Understanding why do varicose veins come back requires identifying whether residual reflux, a recanalised treated vein or a different source is responsible for the recurrence.
For a closer look at the recommended approach to assessment and referral, see the NICE guidance on varicose veins. The guidance explains the role of specialist vascular assessment and duplex ultrasound in people with primary or recurrent varicose veins.
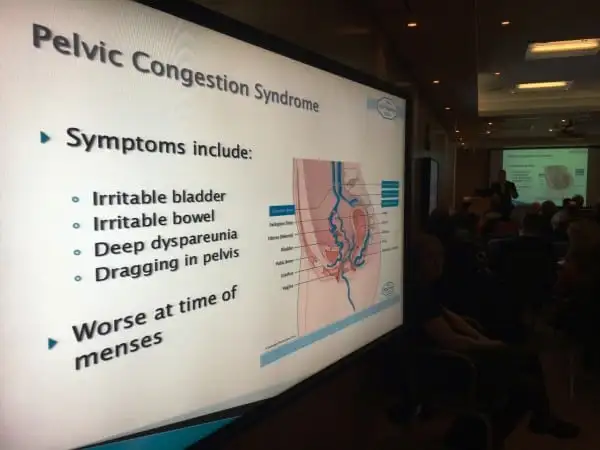
Another possible explanation for why do varicose veins come back is pelvic venous reflux.
Pelvic veins can become incompetent and allow abnormal blood flow towards the lower limbs. This can produce varicose veins in the legs, particularly in some women who have had pregnancies. pelvic venous reflux as a potential contributor to recurrent varicose veins and note its particular association with multiparous women.
Research published by The Whiteley Clinic in 2014 investigated women with recurrent leg varicose veins following previous treatment. The study reported pelvic venous reflux as an important potential source of recurrence and highlighted the need to consider pelvic veins in selected patients.
However, pelvic imaging is not required for every patient with varicose veins. The decision should depend on the clinical history and findings from the vascular assessment and duplex scan.
Interested in the research behind pelvic venous reflux and recurrent leg varicose veins? Read the full Whiteley Clinic research article on pelvic veins.
Perforator veins provide a connection between the superficial and deep veins of the leg. When their valves become incompetent, blood can flow from the deep veins towards the superficial veins. These vessels can form part of a wider reflux pattern and may contribute to persistent or recurrent varicosities in selected patients.
A randomised clinical trial published in 2007 examined what happened to incompetent perforator veins after great saphenous vein surgery. The study found that many incompetent perforators remained detectable after standard treatment. However, the findings should not be interpreted as proof that every incompetent perforator requires treatment. Current guidelines recommend considering perforator treatment in specific clinical situations, particularly when an incompetent perforator represents the source of symptomatic recurrent tributaries.
Research from The Whiteley Clinic has also investigated the role of incompetent perforators and the TRLOP (TransLuminal Occlusion of Perforators) technique. The clinic's published review discusses research suggesting that significant incompetent perforators can form part of the reflux pathway in patients with recurrent varicose veins.
For more detail on this research, read the Whiteley Clinic's article on incompetent perforator veins and recurrent varicose veins.
Yes. Recanalisation is another recognised mechanism of recurrence. It occurs when a previously treated venous segment partially or completely reopens and reflux returns.
This mechanism differs from neovascularisation, in which new small refluxing vessels develop around a previous treatment site. The two processes can occur after different types of intervention and can produce recurrent varicosities through different pathways.
Disease progression can also create new reflux in a vein that was previously healthy. Consequently, a patient may develop new varicose veins even when the original treated vein remains successfully closed.
This distinction is important when considering why do varicose veins come back. A new visible vein does not necessarily mean that the previously treated vein has reopened.
The treatment needs to match the patient's venous anatomy and reflux pattern.
NICE recommends endothermal ablation for people with confirmed varicose veins and truncal reflux when the procedure is suitable. When endothermal treatment is unsuitable, clinicians can consider ultrasound-guided foam sclerotherapy. If foam sclerotherapy is also unsuitable, clinicians can consider surgery.
Modern guidelines also support treatment planning based on the specific source and extent of reflux rather than applying one technique to every patient. The SVS/AVF/AVLS guidelines recommend treating the refluxing venous trunk and associated varicosities according to the patient's anatomy and clinical presentation.
Understanding why varicose veins come back also means considering whether the original treatment matched the underlying pattern of venous reflux. Therefore, the most appropriate treatment cannot be selected reliably from the appearance of surface veins alone. Duplex findings should guide the treatment strategy.
There is no way to guarantee that varicose veins will never return. Venous disease can progress, and new reflux can develop years after treatment. NICE also advises that recurrent varicose veins can occur after treatment and require appropriate reassessment.
However, careful assessment can reduce the risk of leaving significant reflux untreated.
A structured approach should include a clinical examination, a comprehensive duplex ultrasound assessment and identification of the source of reflux. Clinicians should also review any previous treatment. If the findings suggest pelvic venous disease, perforator incompetence or recanalisation, further assessment may be appropriate.
Ultimately, why do varicose veins come back has several possible answers. The visible veins are only part of the picture. Identifying the underlying reflux pathway is the key to selecting an appropriate treatment and managing recurrent disease more effectively.